Pharmacology of Bone Metabolism Drugs: Mechanisms, Uses, and Safety
What if two drugs can both strengthen bone yet act in almost opposite ways? That distinction is central to the pharmacology of bone metabolism drugs: some treatments reduce bone resorption, while others promote bone formation or influence both sides of remodeling. When drug names, targets, and safety cautions blur together, it’s easy to lose sight of how each class works and why those differences matter.
If you find it challenging to connect a drug’s mechanism with its effects on bone remodeling, you’re not alone. This guide organizes major classes by target, action, and clinical context, while keeping important safety principles in view. It’s a framework for learning, not a substitute for current clinical references or individualized medical judgment.
We’ll compare bisphosphonates and denosumab with bone-forming therapies, explain how their mechanisms differ, and highlight class-specific cautions. Short reviews, flashcards, quizzes, and case studies can help you revisit complex mechanisms in manageable steps and give each drug class a distinct place in your understanding.
Key Takeaways
- Use the balance between bone formation and resorption to understand why different drug targets produce different effects.
- Trace RANKL signaling to osteoclast activity to clarify how key antiresorptive agents work.
- Compare each class by target, pharmacologic effect, and clinical context rather than grouping drugs by name alone.
- Separate common adverse effects from serious risks, and connect safety cautions with appropriate monitoring principles.
- Make the pharmacology of bone metabolism drugs easier to recall with a study card for each class: target, effect, use, and risk.
What Bone Metabolism Means, and Why Drug Mechanisms Matter
Bone is living tissue, continually renewed through bone remodeling. In this coordinated process, old or damaged bone is removed through resorption and replaced through formation. Different cell types carry out these activities. Their coordination helps maintain the skeleton, but remodeling is not simply a switch that turns bone loss or growth on and off. The sequence, pace, and balance of resorption and formation all matter.
How normal bone remodeling maintains skeletal tissue
The cycle begins when osteoclasts attach to a bone surface and break down a small area of existing tissue. This is resorption. Osteoblasts then build new bone matrix in that space, supporting its subsequent mineralization. The processes are linked: resorption creates the site for replacement, and formation replenishes it. If removal exceeds replacement, or vice versa, over time the imbalance can alter bone mass and structure.
Osteocytes, mature cells embedded within bone, help coordinate remodeling. They sense mechanical forces and respond to signals related to the body’s metabolic state, influencing communication between bone-forming and bone-resorbing cells. They are not the only influence: age, hormones, health conditions, and other factors can also affect skeletal tissue. Bone strength reflects more than a single measure or process, and a change in remodeling does not point to one cause by itself.
How pharmacologic targets alter remodeling
For the pharmacology of bone metabolism drugs, this cellular sequence provides a practical map. Antiresorptive drugs reduce osteoclast-mediated breakdown or the signals that support it. Bone-forming, or anabolic, drugs promote new bone formation through different targets. These are broad pharmacologic categories, not interchangeable descriptions. Suppressing resorption is not the same action as stimulating formation, even if both approaches may be used to improve skeletal outcomes in appropriate clinical contexts.
A drug’s molecular target helps predict which part of remodeling it affects. A medicine that interferes with a signal needed for osteoclast development or activity is expected to reduce resorption. A medicine acting on pathways that promote osteoblast activity may support formation. Some agents influence remodeling in more than one way, so learn the target and overall effect together. A bisphosphonate overview illustrates one major antiresorptive class and its mechanisms.
This target-first approach makes class distinctions easier to retain: identify the cell or signal a drug affects, then connect that action to resorption, formation, or both. For a refresher on terms such as mechanism of action and drug target, the comprehensive pharmacology guide provides a useful foundation. With that vocabulary in place, compare how individual drug classes act on their molecular targets.
How Major Bone Metabolism Drugs Work at Their Molecular Targets
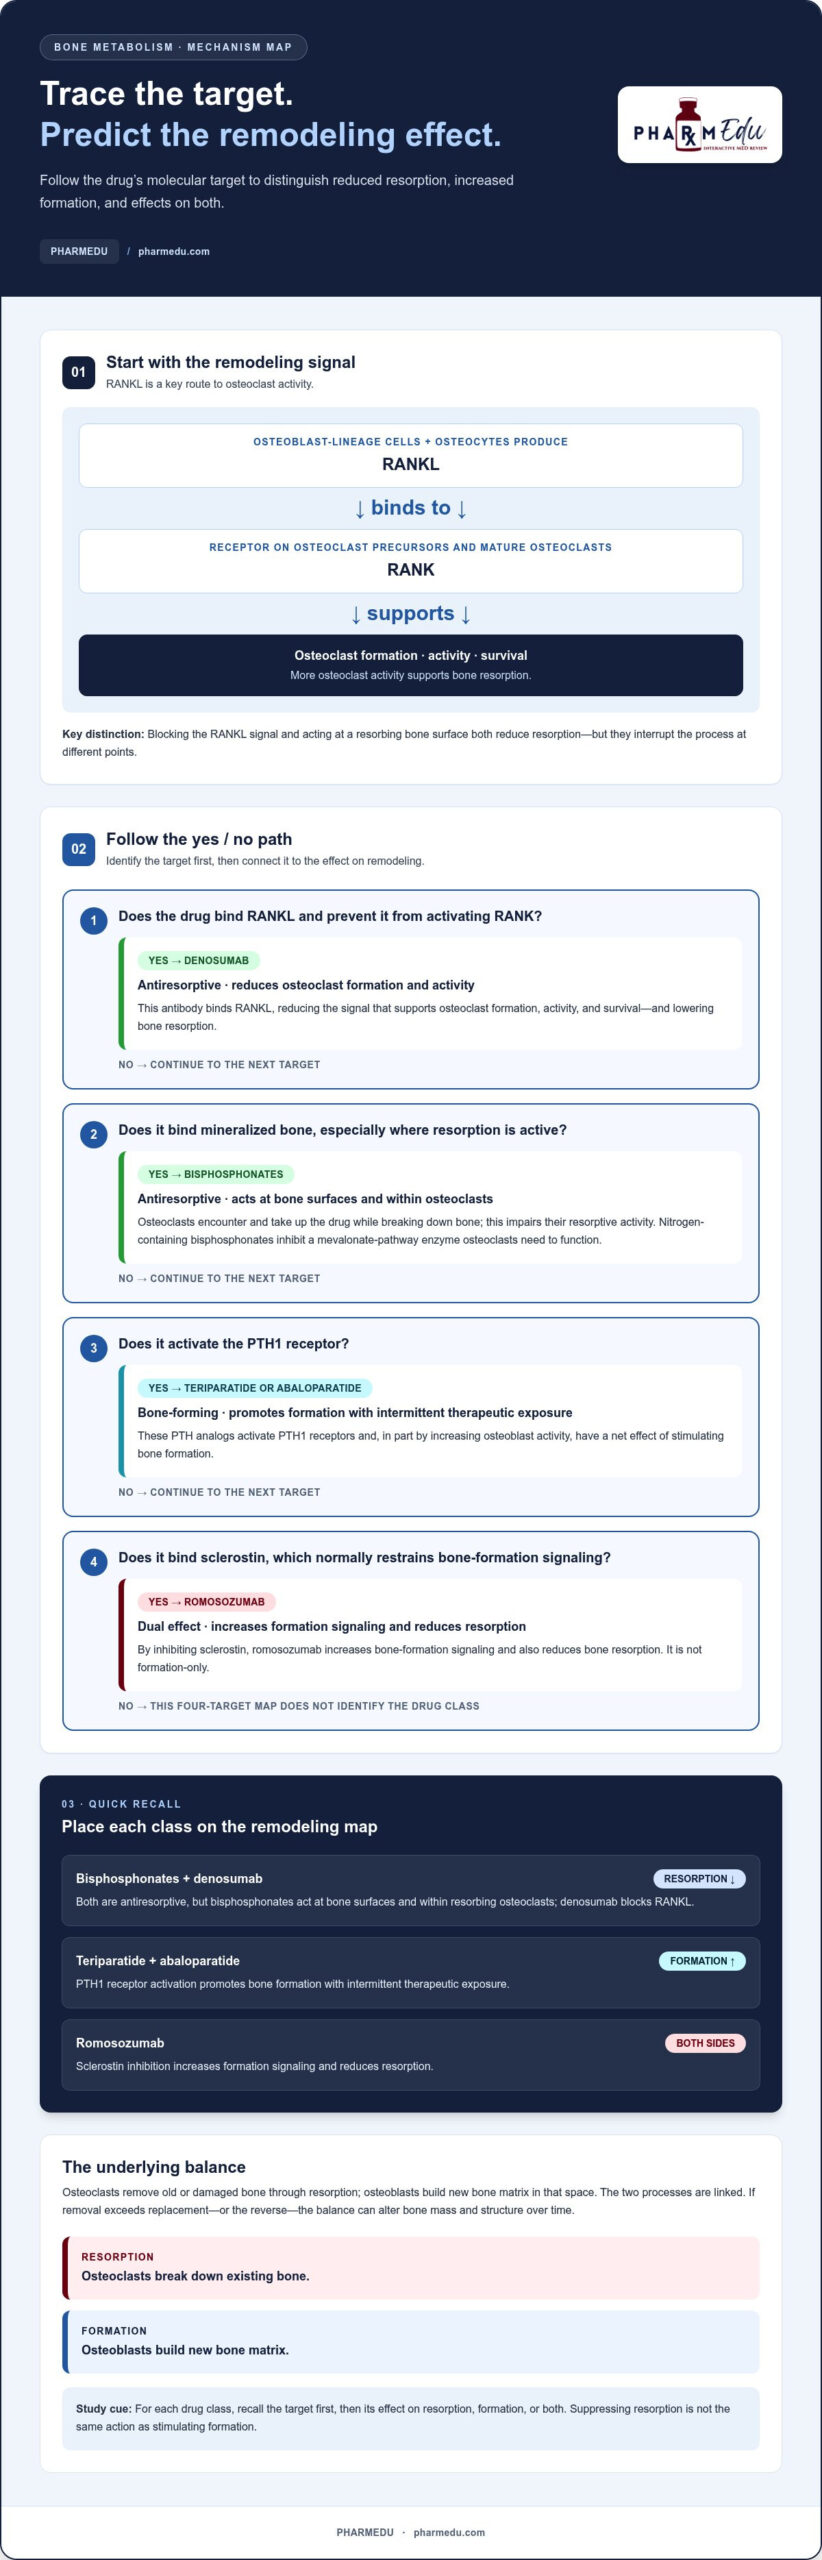
To compare mechanisms, start with the signal that helps regulate osteoclasts. Osteoblast-lineage cells and osteocytes produce receptor activator of nuclear factor kappa-B ligand, or RANKL. When RANKL binds its receptor, RANK, on osteoclast precursors and mature osteoclasts, it supports osteoclast formation, activity, and survival. Blocking this pathway reduces resorption, but different drugs interrupt remodeling at different points. That distinction is central to the pharmacology of bone metabolism drugs.
Antiresorptive mechanisms: bisphosphonates and denosumab
Bisphosphonates bind to mineralized bone, particularly at sites undergoing active resorption. As osteoclasts break down bone, they encounter and take up the drug, which impairs their resorptive activity. Nitrogen-containing bisphosphonates inhibit an enzyme in the mevalonate pathway that osteoclasts need to function. Their action is linked to bone binding and effects within osteoclasts, not to neutralizing RANKL.
Denosumab acts differently. This antibody binds RANKL, preventing it from activating RANK. With that signal reduced, osteoclast formation and activity decline, lowering bone resorption. A useful recall distinction is that bisphosphonates act at bone surfaces and within resorbing osteoclasts, while denosumab blocks a signal that promotes osteoclast development and function. Their targets, administration, and effects after discontinuation are not interchangeable, so keep those differences clear when comparing classes.
Bone-forming and other mechanisms: PTH analogs and romosozumab
Teriparatide and abaloparatide activate the PTH1 receptor. With intermittent therapeutic exposure, their net effect is to stimulate bone formation, in part by increasing osteoblast activity. The key study point is that these analogs are not simply antiresorptives: their formation-promoting effect distinguishes them from drugs that primarily suppress osteoclast-mediated breakdown.
Romosozumab binds sclerostin, a protein that normally restrains signaling involved in bone formation. Sclerostin inhibition increases bone formation signaling and also reduces bone resorption. This dual effect means romosozumab does not fit neatly into a formation-only category. Its influence on both sides of remodeling is an important mechanism-level distinction.
For efficient recall, connect each agent to its target first, then state whether its dominant effect is to reduce resorption, promote formation, or influence both. Short review activities, such as PharmEDU’s interactive pharmacology flashcards, can help you revisit these target-effect links. Use them as study support alongside current clinical references. This framework prepares you to compare classes by clinical context and safety without confusing their mechanisms.
How Bone-Active Drug Classes Differ in Clinical Context
Osteoporosis offers a familiar context for comparing bone-active therapies, but a shared clinical area does not make these drugs interchangeable. Their targets and remodeling effects differ, and approved indications and place in therapy depend on the specific drug, patient, and current guidance. The table is a mechanism-based study comparison, not a treatment algorithm or ranking of options.
| Class | Target | Remodeling effect | Study distinction |
|---|---|---|---|
| Bisphosphonates | Bone mineral and osteoclast activity | Reduce osteoclast-mediated resorption | Act at bone surfaces and within resorbing osteoclasts. |
| Denosumab | RANKL | Reduces osteoclast formation and activity, lowering resorption | Blocks a signal that supports osteoclasts rather than acting like a bisphosphonate at bone surfaces. |
| PTH analogs, including teriparatide and abaloparatide | PTH1 receptor | Promote bone formation with intermittent therapeutic exposure | Distinguish their formation-promoting effect from primarily antiresorptive action. |
| Romosozumab | Sclerostin | Increases bone formation and reduces resorption | Has effects on both sides of remodeling. |
The comparison helps explain what each class does, but not which one is appropriate for a particular person. Clinical context may include fracture risk, prior treatment, relevant health conditions, and other patient-specific considerations. These factors shape prescribing decisions and require clinical assessment; a mechanism alone cannot determine the choice.
Therapy may also be considered in sequence. For example, guidance may recommend an anabolic agent for selected patients at very high fracture risk, followed by an antiresorptive drug to help maintain bone gains. This illustrates why the effect of a medicine during treatment and the plan after it are separate learning points. It does not mean every patient should follow the same sequence.
The pharmacology of bone metabolism drugs is easier to compare when you keep two questions separate: “What does the drug target?” and “In what clinical context might it be used?” The first is a pharmacologic question; the second depends on current recommendations, the drug’s approved indications, and individual circumstances. Guidance and labeling can change, and recommendations may differ across populations. Verify these details against current authoritative references before applying them in practice or study.
Use the table as a starting point for recall, not as a prescribing shortcut. If two medicines share a broad effect, compare their molecular targets and clinical uses rather than grouping them together. This preserves important distinctions while keeping treatment decisions grounded in current clinical guidance and individualized care.
Safety, Adverse Effects, and Monitoring: What Learners Should Separate
Safety is easiest to study when you separate expected or relatively common adverse effects from uncommon but serious risks, then connect each concern to the specific drug. Bone metabolism drugs have distinct targets and precautions, so do not assume a warning for one class applies to all bone-active therapies. Risk assessment depends on the drug, dose and duration, kidney function, calcium status, fracture and cardiovascular history, and other patient-specific factors.
Recognize class-specific safety issues
Oral bisphosphonates can cause upper gastrointestinal irritation, while intravenous forms may produce a transient flu-like reaction. Less frequent but important concerns include osteonecrosis of the jaw and atypical fractures. The FDA updated warnings for several bisphosphonates in February 2026, broadening atypical-fracture information beyond the thigh to include bones such as the lower leg and arm. Distinguish these risks from routine tolerability issues rather than treating them as equally common.
Denosumab has a different serious risk profile. The FDA’s January 2024 boxed warning highlights severe hypocalcemia in patients with advanced chronic kidney disease, particularly those receiving dialysis. Discontinuation is another distinct consideration: bone turnover can rise after denosumab is stopped, with increased risk of vertebral fractures. Treatment planning around discontinuation matters; this is not a generic effect shared by all antiresorptives.
For PTH analogs, the FDA required updated label warnings in August 2026 about serious hypersensitivity reactions, including anaphylaxis and angioedema. Romosozumab has a cardiovascular safety warning; its prescribing information calls for attention to myocardial infarction and stroke risk. These examples show why you should check the relevant label for the specific agent and current jurisdiction.
Understand monitoring without turning it into a prescription
When assessing risk, clinicians may consider kidney function, serum calcium, vitamin D status, fracture history, cardiovascular history, concurrent medicines, and dental health. The relevance of each factor differs by drug and patient. For example, advanced kidney disease is central to the FDA’s denosumab hypocalcemia warning, while cardiovascular history is pertinent to romosozumab risk assessment. These are examples of clinical considerations, not a universal monitoring checklist.
Laboratory testing and imaging follow-up depend on the indication, medicine, patient’s clinical circumstances, and current guidance. Do not assume every patient needs identical tests or testing intervals. Interpret adverse effects and safety signals using current prescribing information and authoritative clinical references, not an educational summary alone. This section supports learning; it does not replace professional judgment or advise anyone to start, stop, or change treatment.
Strengthen your recall of class-specific distinctions with PharmEDU’s pharmacology practice quizzes, alongside current clinical references.
A Practical Study Framework for Bone Metabolism Drugs
Build each drug-class summary in the same order. This turns the pharmacology of bone metabolism drugs into connected facts rather than a list of names to memorize. Keep the mechanism concise, then use current references to verify clinical indications and safety details, which can vary by agent and change as guidance is updated.
Use a four-part recall sequence for each drug class
Create a card with four prompts. Answer from memory before checking your notes, then fill any gaps using an authoritative, current reference. This helps distinguish what a drug does from the context in which it may be used.
- Target: Name the molecular target or pathway, such as RANKL, the PTH1 receptor, or sclerostin.
- Effect: State whether the dominant remodeling effect is reduced resorption, increased formation, or an effect on both.
- Use: Record the broad clinical context, then verify the approved indication and place in therapy for the specific drug and population.
- Risk: Add one safety distinction that is particularly relevant to that class, and check the current prescribing information for details.
For example, a denosumab card might prompt you to recall RANKL as the target and reduced osteoclast activity as the effect, while marking the appropriate indication as a reference-check item. Its risk prompt can help you distinguish severe hypocalcemia concerns in advanced chronic kidney disease from the separate planning considerations around discontinuation. The card is a memory aid, not a patient-specific recommendation.
Keep entries brief enough to review quickly but specific enough to expose confusion. If you can name a drug’s effect but not its target, or recall a caution but attach it to the wrong class, revise the card. Avoid writing “bone drug” as the category: identify the class so you do not transfer one medicine’s mechanism or warning to another.
Reinforce pharmacology knowledge with structured review
Use retrieval practice: close your notes, explain the target and effect aloud, then check your accuracy. Follow with a short case vignette that asks which class-level mechanism fits a described situation. Focus on pharmacology, not on selecting treatment for a real person. Educational exercises do not provide medical consultation, and clinical decisions require current references and professional judgment.
For a broader approach to reviewing drug concepts, the pharmacology study guide for nursing students can complement this mechanism-to-class framework. PharmEDU offers short video vignettes, interactive flashcards, content reviews, quizzes, and case studies across over 100 pharmacology topics. The mobile-compliant platform uses micro-learning segments, so you can revisit challenging concepts in short study sessions. These formats support repeated review; they are not a substitute for prescribing information or clinical references.
Choose a format that fits the task: use a video vignette to revisit a concept, a flashcard to retrieve a target-effect link, or a quiz or case study to test recall. Explore PharmEDU’s pharmacology review for flexible micro-learning that supports ongoing study.
Keep Building Confidence Through Focused Review
Use your next study session to strengthen how you reason through unfamiliar drug mechanisms. Recall the target, explain its effect on remodeling, then check whether you can distinguish the relevant clinical context and safety considerations. Repeating this process makes the pharmacology of bone metabolism drugs easier to retrieve in learning situations, while current clinical references remain essential for recommendations and prescribing decisions.
For continued, self-paced pharmacology review, PharmEDU offers over 100 topics with educational content created by physicians, pharmacists, and instructional designers. Short learning formats help you revisit challenging concepts and build your knowledge over time.
Explore PharmEDU’s pharmacology review and take your next step toward more confident, well-structured study. Every focused review is progress.
Frequently Asked Questions
What is the difference between bone resorption and bone formation?
Bone resorption removes existing bone tissue, while bone formation adds new bone matrix. Both are part of remodeling, and many bone-active medicines influence one process more strongly than the other. To study a drug, ask which cell or signal it affects, then connect that target to resorption or formation. This gives you a practical way to distinguish classes rather than relying on drug names alone.
Which medications are considered antiresorptive drugs?
Bisphosphonates and denosumab are major antiresorptive classes because they reduce osteoclast-mediated bone breakdown. Other agents may also have antiresorptive effects in particular settings, so do not classify a medicine based only on a broad label or a single remembered effect. Check the specific drug’s current prescribing information and an authoritative reference for its class, approved indications, and role in care. Details may vary across medicines and patient groups.
How does denosumab differ from a bisphosphonate?
Denosumab is a monoclonal antibody that blocks RANKL, while bisphosphonates inhibit osteoclast-mediated resorption through a different mechanism. Both are antiresorptives, but that shared category does not make their pharmacology identical. Test your recall by explaining each target without notes, then identify which class blocks a signaling molecule and which acts through effects associated with bone surfaces and osteoclasts.
Can bone metabolism drugs increase bone formation?
Yes. Teriparatide and abaloparatide are PTH analogs associated with bone-forming effects, while romosozumab inhibits sclerostin and affects remodeling through that pathway. These agents are not interchangeable: their mechanisms, approved uses, precautions, and place in therapy differ. For study or practice, verify the current prescribing information for the specific medicine rather than assuming one drug’s indication or safety details apply to another.
What happens when denosumab treatment is stopped?
Stopping or delaying denosumab can have important bone-health implications, including a rise in bone turnover and increased risk of vertebral fractures after discontinuation. The next steps depend on clinical circumstances and require professional judgment. Do not treat a missed or planned dose as a routine medication adjustment, or use a general educational explanation to make an individual plan. Current clinical guidance and the treating professional are essential for decisions about ongoing care.
Are bone metabolism drugs used only for osteoporosis?
No. Bone-active medicines may be used in different clinical contexts, depending on the individual drug and its approved indications. The term describes a broad pharmacologic area, not a diagnosis or treatment plan. For any medicine, check the current label to confirm which conditions it is approved to treat and for which populations. A mechanism can help explain how a drug works, but it does not establish appropriate clinical use by itself.
How can I remember the major bone metabolism drug classes?
Build a short recall card for each class: target, remodeling effect, broad clinical context, and one safety distinction. Test yourself by explaining the card aloud before checking your notes. For example, compare two drugs with an antiresorptive effect and identify how their targets differ. Brief flashcard reviews, quizzes, or case-based questions can expose gaps, while clinical decisions still require current references and professional judgment.